
Tapering off opioid pain medication
Whether you were given oxycodone after an operation or have been on a daily opioid for years, coming off works better as a planned reduction than as a decision made on a bad morning.
What opioids are, and why they are prescribed
Opioids are the strongest pain medications in routine use. They are prescribed after surgery and injury, for cancer pain, and for chronic pain when other treatments have not been enough. For acute pain they are usually the right answer, and for some people long-term opioid therapy remains appropriate.
Two situations bring people here. The first is post-surgical: a prescription that was meant to cover a couple of weeks, and a wish to stop before it becomes something harder to stop. The second is long-term: years on a daily opioid, a growing sense that it is doing less for the pain than it used to, and no clear route down.
Both are ordinary clinical situations. Neither requires you to have done anything wrong.
Generic and brand names
Buprenorphine and methadone appear here because they are prescribed for pain as well as for opioid use disorder. If you are taking either as treatment for a substance use disorder, that care belongs with an addiction specialist rather than with us — tell us at intake and we will help you find the right service.
| Generic name | Common brand names | Typically prescribed for |
|---|---|---|
| Oxycodone | OxyContin, Roxicodone, Oxaydo; with acetaminophen: Percocet | Moderate to severe pain, including after surgery |
| Hydrocodone | With acetaminophen: Norco, Vicodin, Lortab; extended release: Hysingla ER | Moderate to severe pain |
| Tramadol | Ultram, ConZip, Qdolo | Moderate pain |
| Morphine | MS Contin, Arymo ER, Kadian | Severe or ongoing pain |
| Hydromorphone | Dilaudid | Severe pain |
| Codeine | Tylenol with Codeine No. 3 and No. 4 | Mild to moderate pain, cough |
| Oxymorphone | Opana ER | Severe ongoing pain |
| Fentanyl | Duragesic (patch), Actiq, Subsys | Severe ongoing pain when other opioids are not sufficient |
| Tapentadol | Nucynta | Moderate to severe pain, diabetic nerve pain |
| Methadone | Dolophine, Methadose | Severe ongoing pain; also opioid use disorder |
| Buprenorphine | Butrans (patch), Belbuca | Ongoing pain; also opioid use disorder |
What long-term use can look like
The effects below build gradually, which is what makes them easy to miss. Several of them improve as the dose comes down.
The dose that used to control the pain controls less of it. Increasing the dose restores the effect for a while, and then the cycle repeats.
Long-term opioid use can make the nervous system more sensitive to pain rather than less. Some patients report less pain after a taper than during it.
Persistent, does not improve with time on the medication, and for many people the most wearing day-to-day effect.
Suppressed testosterone and other hormonal changes, with knock-on effects on energy, mood, libido and bone density.
Slowed thinking and reaction time, with implications for driving and work.
Long-term opioid use is associated with sleep-disordered breathing, and the risk rises sharply if a benzodiazepine or another sedative is taken alongside.
What stopping abruptly can feel like
Opioid withdrawal is rarely life-threatening in an otherwise healthy adult, but it is genuinely miserable — and being ambushed by it is the most common reason a self-managed attempt ends in going back to the previous dose.
An inability to sit still, agitation, and a strong sense of dread. Often the first sign, and it starts earlier than people expect.
Deep aching in the back, legs and joints, sometimes with cramping and involuntary leg movements.
Nausea, vomiting, abdominal cramping and diarrhea, which together can cause real dehydration.
Alternating hot and cold, drenching sweats, and skin that crawls.
Cold-like symptoms with no infection behind them.
Little sleep for several nights, and pain that feels worse than it did before — partly rebound, and partly a nervous system that has become more pain-sensitive.
Before you change anything
This page is general information about a group of medications. It is not medical advice about you, and it is not a reason to change a dose on your own.
Several of the medications Prescriby Health tapers can be dangerous to stop abruptly. If you are in withdrawal now, contact your prescriber or an urgent care service today. If you feel unsafe, call 911. For mental-health crisis support in the US, call or text 988.
How we taper opioids
The first thing your provider establishes is what the pain actually needs now, which is not necessarily what it needed when the prescription started. The taper is written around that, not around a fixed timetable.
For someone who has just had surgery, the reduction can often be quick — weeks — because the pain that justified the opioid is genuinely resolving. For someone who has been on a daily dose for years, the sensible pace is much slower: modest percentage reductions, held for as long as they need to be held, with the option of pausing entirely if life gets in the way.
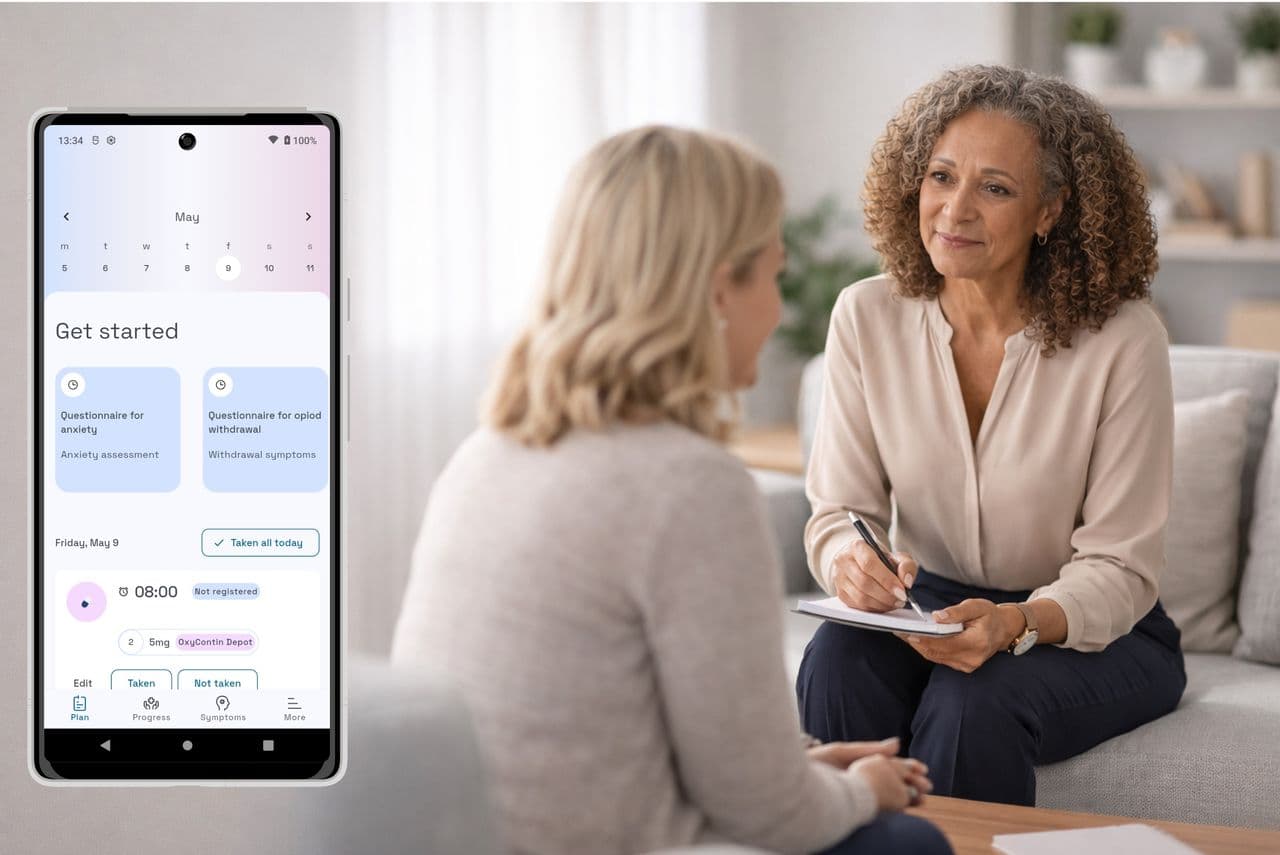
We take over prescribing the opioid being reduced for the duration of the taper, which removes the refill anxiety that makes tapering harder than it should be. You log pain and symptoms between visits in the Prescriby app, and we adjust. If the pain needs something else alongside the reduction, that is part of the conversation rather than an afterthought.
Learn more
Related reading on tapering and on how the program works.
Intake, the taper schedule, follow-up intervals, cost, and who the program is and is not right for.
The six groups we work with, with generic and brand names for each.
Clinical insight, patient stories and company news from Prescriby Health.
Questions about opioids
Not necessarily, and often the opposite. Long-term opioid use can increase sensitivity to pain, so some patients find their pain is no worse — and occasionally better — at a lower dose. What is common during the reduction itself is a temporary increase, which is why the steps are small and why we adjust the pace to what you report.
If your pain genuinely needs treatment, tapering the opioid does not mean leaving it untreated. That is part of the plan, not an omission from it.
Usually not. Post-surgical tapering is one of the clearest cases for acting early: the pain that justified the prescription is resolving, and a short structured reduction now avoids the much harder job of stopping after months. Ask us — or ask your surgeon to refer you.
Most people on long-term opioids are physically dependent, which is an expected consequence of the medication rather than a behavioral disorder. Dependence means withdrawal on stopping. Addiction means compulsive use, craving, and continuing despite harm.
Some people have both, and that is not a reason to avoid asking for help — it changes what the right help is. If there is a pattern of misuse, tell us at intake so we can either build it into the plan or refer you to a service better suited to it.
Post-surgical tapers are often measured in weeks. Long-term tapers are measured in months, and how many depends on the dose, how long you have taken it, and how the early steps go. Your schedule is set at intake and revised as you go.
No. Reducing to a lower, more sustainable dose is a legitimate goal and for some patients it is the right one. You decide what success looks like, and the plan is written to that.
Ready to talk about opioids?
Tell us the name on the box and how long you have been taking it. We will tell you what a taper would look like.
You do not need a referral. Providers are welcome to refer directly.